
Achilles tendinopathy is one of those conditions every sports medicine team knows too well. Around 6% of people will have it at some point in their lives, 38% of workers affected report reduced work capacity, and exercise-based rehabilitation, the recommended first-line treatment, does not resolve the problem in up to 44% of cases. While I personally solved such issues always with resistance exercise, almost half of those with persistent symptoms go on to seek other treatments, and injections are a common next step. One of the most popular over the last 15 years has been the high-volume injection: 50 mL of fluid pushed in between the tendon and the fat pad that sits in front of it, often with a corticosteroid added.
A randomised controlled trial just published in The BMJ by Peter Malliaras and colleagues, the Inject trial (28 October 2026), gives us the best data so far on whether these injections work. The headline is clear: at 12 months there was no difference between treatments. Neither the high-volume injection with corticosteroid nor the one without it improved pain and disability compared with a sham injection, and the two injections did not differ from each other.
What the trial did
The team randomised 192 adults with midportion Achilles tendinopathy at a radiology clinic in Melbourne between December 2019 and July 2022, recruited mainly through paid social media advertising and referrals from local doctors and physiotherapists. These were not mild cases: mean age 49, 55% men, a median symptom duration of two years, a baseline VISA-A score of 48.7 out of 100, about half with symptoms in both legs and a third with obesity. Everyone had pain for at least three months, ultrasound evidence of tendon pathology (hypoechoic areas and/or Doppler signal), and had not responded to previous treatment; almost 80% had already tried exercise.
Participants were randomised 1:1:1 to one of three arms:
- Sham injection (n = 64)
- High-volume injection without corticosteroid (n = 63)
- High-volume injection with corticosteroid (n = 65)
Crucially, everyone then received the same care from a physiotherapist: a progressive 12-week calf and Achilles loading programme, education on activity modification using a pain-monitoring model, and information about the condition and its prognosis. So the question the trial answers is not “injection versus nothing” but “does adding an injection to good rehabilitation make a difference?”. Adherence was high, with 91–95% of participants averaging at least two exercise sessions a week across groups.
The primary outcome was the VISA-A (Victorian Institute of Sport Assessment – Achilles, 0–100, higher is better) at 52 weeks, and the trial was powered to detect a 10-point difference between any two groups. Because there were three pairwise comparisons, the authors used 98.33% confidence intervals and a significance threshold of 0.0167. A full cost-utility analysis from a societal perspective ran alongside, and the statistical analysis plan was published before any analysis started.
The injections, explained
The high-volume injection was introduced by Otto Chan and colleagues in 2008. Its rationale is that part of the pain in Achilles tendinopathy comes from new blood vessels and nerves growing into the front of the tendon from Kager’s fat pad, the triangle of fat between the Achilles, the deep flexor tendons and the heel bone. Injecting a large volume of fluid exactly at that interface is thought to disrupt this neurovascular ingrowth mechanically or by temporarily reducing blood supply, while a corticosteroid, when added, provides an anti-inflammatory effect.
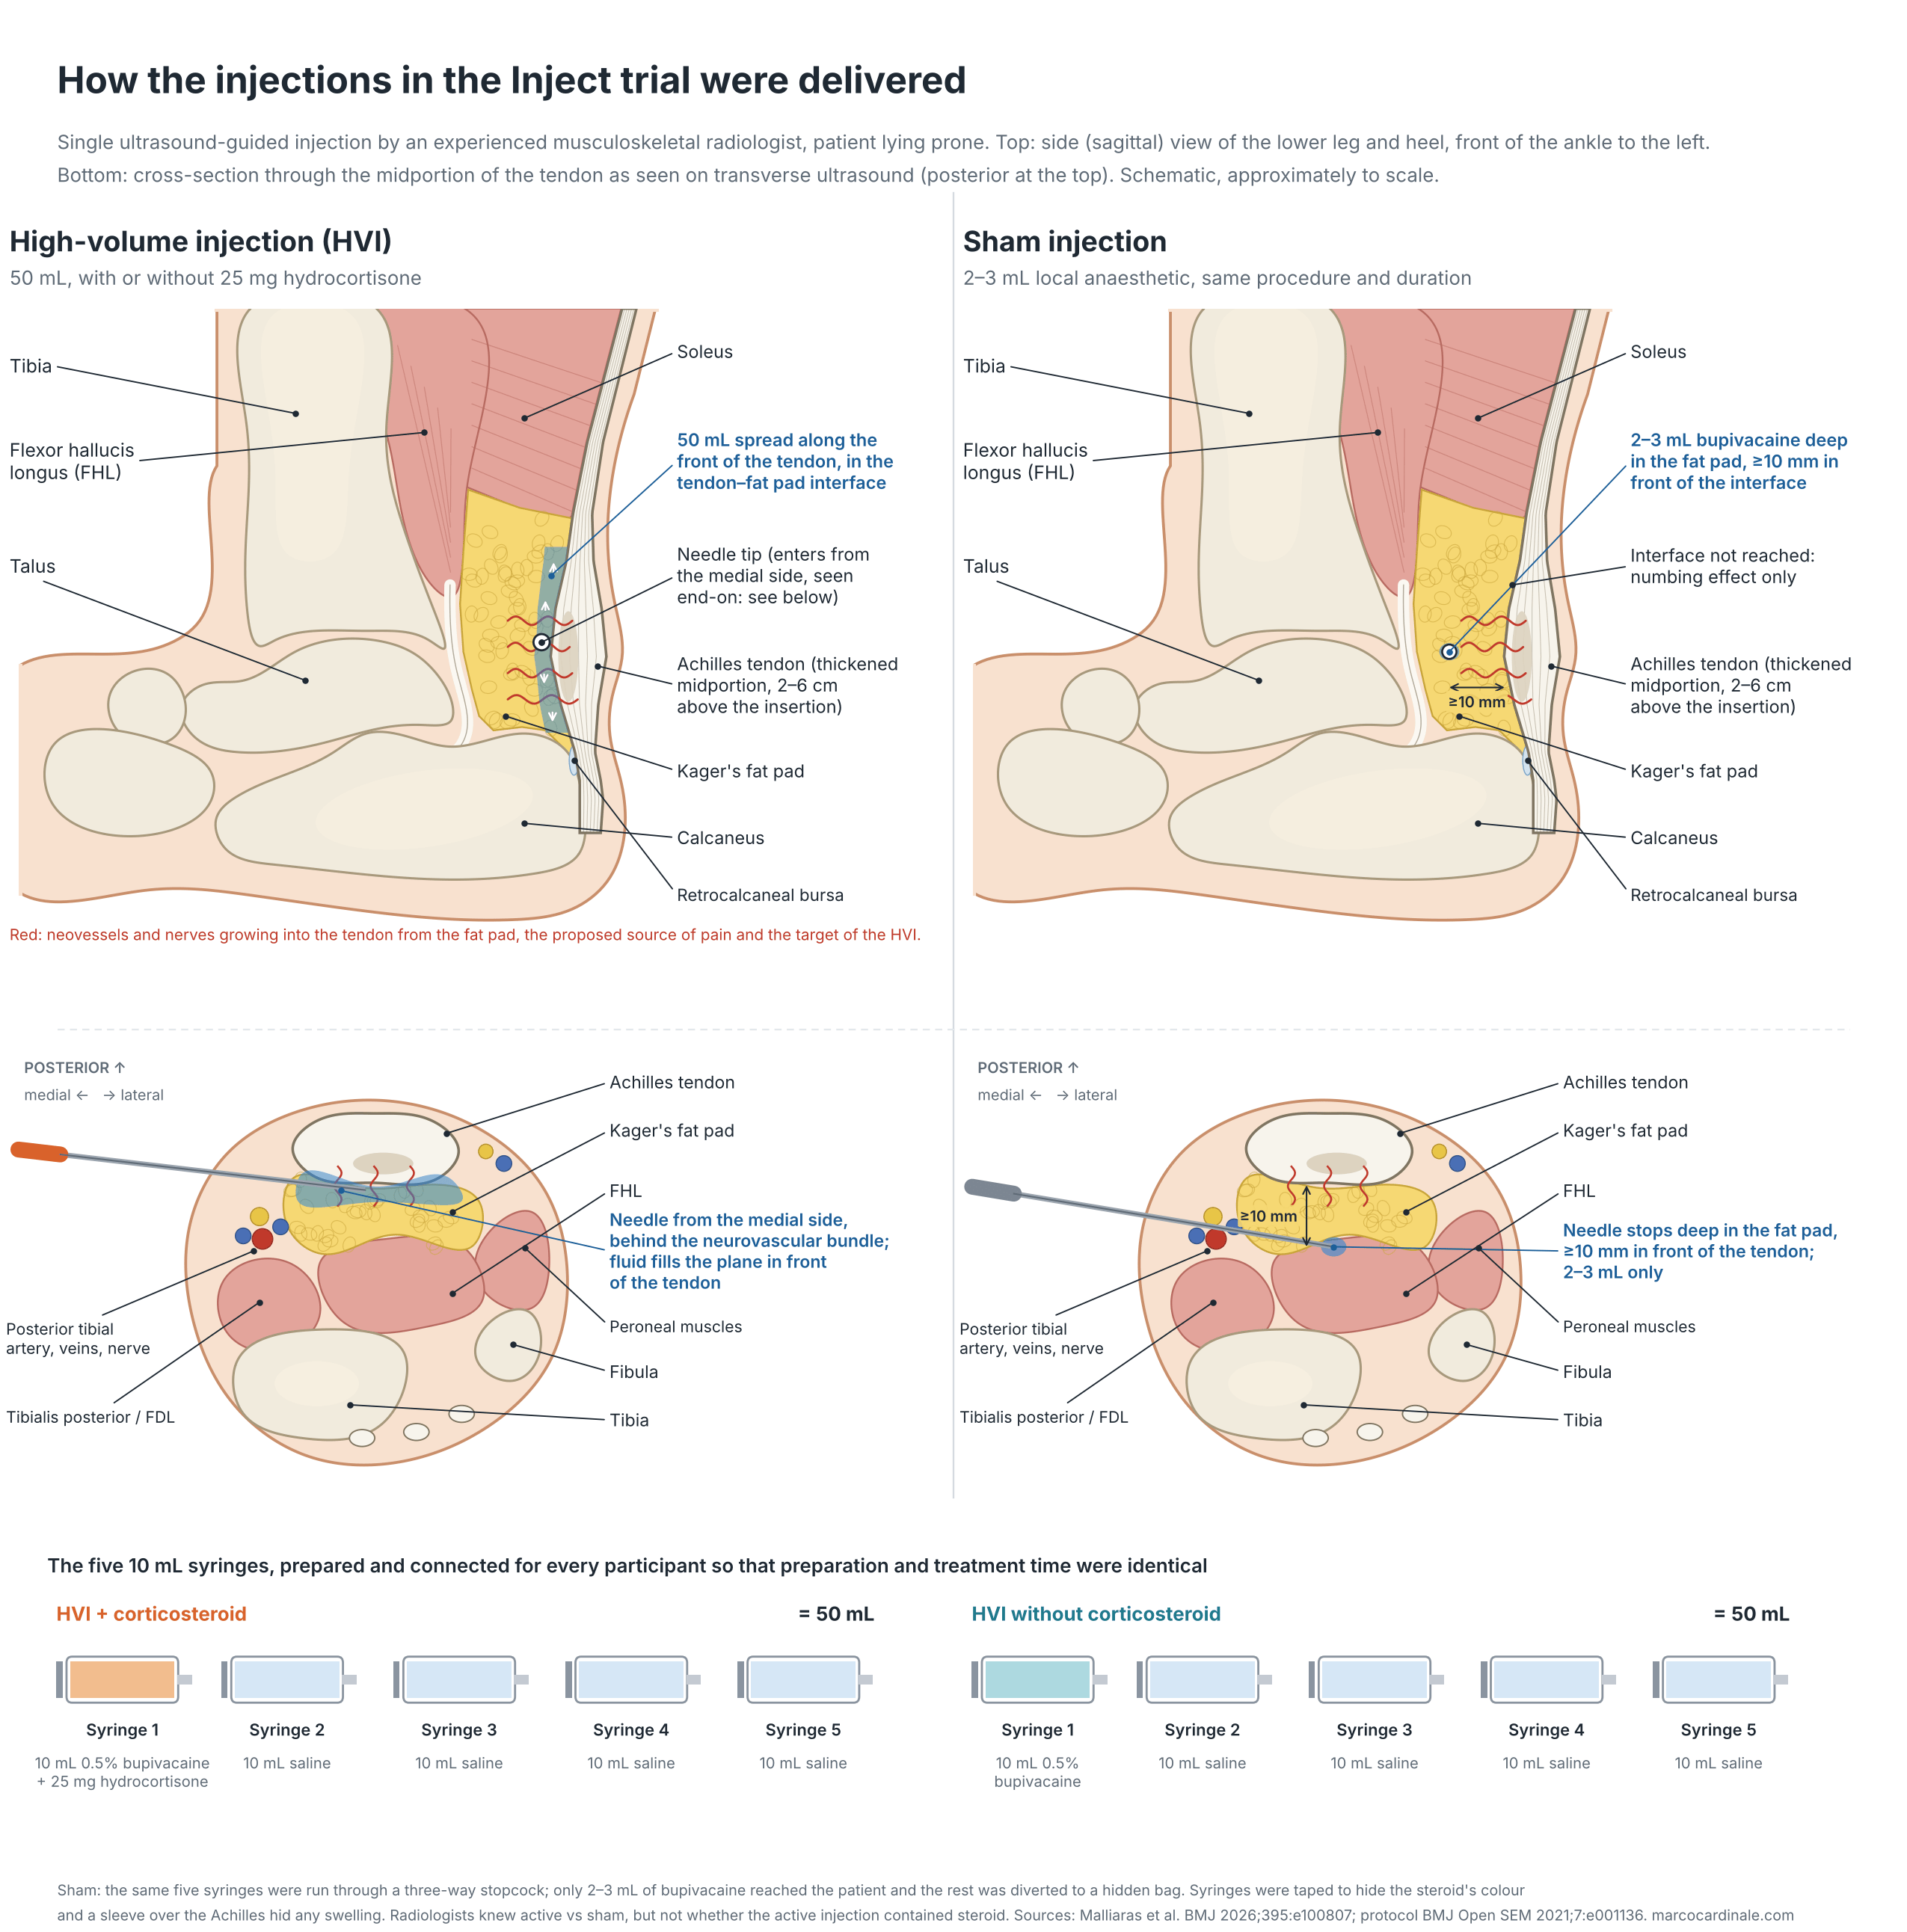
Each participant received a single injection, under ultrasound guidance, from one of three experienced musculoskeletal radiologists, with the patient lying face down. Dr Chan himself travelled to Melbourne to train the radiologists, and 11% of injections were randomly observed to check fidelity. In practice:
- High-volume injection with corticosteroid: five 10 mL syringes connected in sequence through a tube. The first contained 10 mL of 0.5% bupivacaine (a local anaesthetic) with 25 mg of hydrocortisone, followed by four syringes of 10 mL normal saline, for a total of 50 mL. The needle was placed at the interface between Kager’s fat pad and the tendon and moved gently along it, under continuous ultrasound monitoring, to spread the fluid evenly over the pathological area.
- High-volume injection without corticosteroid: identical, except the first syringe contained only the 10 mL of bupivacaine.
- Sham injection: 2–3 mL of 0.5% bupivacaine, injected at least 10 mm anterior to (deeper than) the fat pad–tendon interface, a placement unlikely to be therapeutic. It produces a numbing effect similar to the high-volume injections.
The masking procedures are worth noting. Every participant went through an identical procedure with five 10 mL syringes. In the sham group, a three-way stopcock diverted the fluid to a hidden bag. The syringes were taped so the colour of the steroid could not be seen, and afterwards participants wore a sleeve over the Achilles to hide any swelling from the large volume. The radiologists knew whether they were giving an active or a sham injection, but not whether the active one contained steroid. The check worked: immediately after the injection, 67–73% of participants in each group were unsure what they had received, and only 22–24% in each group believed they had received an active injection.
What each ingredient does
Bupivacaine is a long-acting local anaesthetic. It blocks voltage-gated sodium channels in nerve fibres, so pain signals cannot be transmitted. Its peak effect comes after about 30–45 minutes and the numbness lasts hours, not weeks. In the trial it gave the same numbing sensation in all three arms, which is part of what kept participants unaware of their group. The 50 mg used in the high-volume injections is well below the usual maximum dose of about 2 mg/kg (up to 175 mg), and the sham delivered 10–15 mg.
Hydrocortisone is a corticosteroid. It diffuses into cells, binds the glucocorticoid receptor and switches genes off and on in the nucleus: it dampens the NF-κB-driven production of inflammatory cytokines and COX-2, and increases annexin A1, which blocks phospholipase A2 and therefore the production of prostaglandins and leukotrienes. The net result is less inflammation, less vascular leakage and less pain sensitisation. The same actions have a cost in tendon tissue: injected corticosteroids reduce local collagen production, which can limit healing and leave the tendon more prone to failure. Hydrocortisone is short-acting and the least potent of the injectable steroids: 25 mg is equivalent to about 5 mg of triamcinolone, compared with the 40 mg typically injected into a large joint. Because tendinopathy is thought to be more a failed healing response than classic inflammation, damping that response can ease pain early without rebuilding the tendon.
Saline provides the volume: 40 mL meant to separate the tendon from the fat pad and disrupt the neovessels and nerves, mechanically or by cutting their blood supply. In Inject, the steroid-free injection made no difference to symptoms, Doppler signal or tendon thickness, so the volume on its own seems to be inactive.

What they found: no difference between treatments
Follow-up was excellent, with VISA-A data from 181 of 192 participants (94%) at 12 months. At the primary endpoint there was no difference between any of the groups:
- High-volume injection with corticosteroid vs sham: −3.5 points (98.33% CI −12.0 to 5.0)
- High-volume injection without corticosteroid vs sham: +4.0 points (−4.2 to 12.3)
- With vs without corticosteroid: −7.5 points (−15.3 to 0.3)
The high-volume injection without steroid showed no benefit over sham at any time point, on VISA-A or on any secondary outcome. Ultrasound told the same story: there were no differences in Doppler signal or tendon thickness between this injection and sham. As the authors put it, simply injecting a volume of fluid does not seem to affect tendon pathology or improve clinical outcomes.
The secondary time points showed a pattern worth knowing about, but it needs to be read with caution. With the steroid injection there was a small benefit over sham at six weeks (+9.2 points, 1.5 to 16.9), together with a better global rating of change. By 26 weeks the steroid group was doing worse than the group that had received the same injection without steroid (−8.6 points, −16.4 to −0.7), with higher worst pain over the previous week (11.3 points on a 0–100 scale). All of these differences were smaller than the 10-point target, and the authors note that the early benefit is unlikely to be clinically meaningful and might be no more than chance, given the number of outcomes and time points tested.

Benefits and risks of these injections
Benefits. The case for a corticosteroid-containing injection rests on short-term relief. In the Inject trial this was a 9.2-point VISA-A advantage over sham at six weeks, smaller than the 10-point target and gone by 12 months, along with less time off work early on and lower costs over the year. The procedure is quick, done in one visit and image-guided. The steroid-free injection showed no benefit at any point.
Risks in the trial. There were no Achilles tendon ruptures. Six participants had serious adverse events (two in each group), none related to the trial. Non-serious adverse events were common in all groups (53% sham, 38% without steroid, 49% with steroid), mostly aggravated Achilles pain (28%, 16% and 25%) or other musculoskeletal pain. Only one, injection-site pain after the steroid injection, was judged to be related to the injection itself. The main harm signal was clinical rather than a complication: worse VISA-A and worse pain at 26 weeks with the steroid than without it.
Risks of corticosteroid injections in general. A 2024 review in the American Journal of Roentgenology by Kamel, Rosas and Gorbachova sets out the side effects patients should be told about before a musculoskeletal steroid injection. It also notes that systematic reviews are inconclusive on long-term benefit for joints and tendinopathy, which fits the Inject results. Most of the frequencies below come from mixed injection sites, often joints, rather than from Achilles injections specifically:
- Local: a post-injection flare of pain is common, reported in 33–35% of hand, wrist and shoulder injections, usually starting 1–2 days later and lasting about 2 days. Skin thinning or loss of colour occurs in up to 10% after superficial injections (for example of the plantar fascia), appears within months and usually resolves within a year. Tendon rupture is rare, about 0.1%, typically between 2 days and 6 weeks after the injection, and the Achilles is one of the tendons involved in case reports. Being next to the tendon rather than in it is not a guarantee of safety: in a rabbit study, injection into the retrocalcaneal bursa weakened the Achilles as much as injection into the tendon. Infection after a joint injection is very rare (under 0.001%), and soft-tissue calcification, faster progression of osteoarthritis and bone injury have also been reported, mainly after joint injections.
- Systemic: part of the injected steroid reaches the bloodstream. Cortisol production is suppressed for at least a week after a single injection, and for up to 2 weeks in a study of young athletes. Facial flushing affects about 40% and settles within 3 days. Blood pressure and blood glucose can rise for more than a week. About half of premenopausal women have early or delayed periods afterwards. Allergic reactions (0.3–0.5%), raised eye pressure, insomnia, headache and, with repeated use, bone loss are also described.
- People with diabetes: glucose typically peaks 1–3 days after the injection, and levels up to 500 mg/dL have been reported. The review cites a recommendation to check glucose twice a day for a week, seek help above 360 mg/dL, and avoid injecting if fasting glucose is above 200–250 mg/dL.
- Surgery: injections are linked to more post-operative infections and to more revision surgery after tendon repair. The review suggests delaying surgery for 1–3 months after an injection and withholding steroid for 3–6 months before a tendon repair or joint replacement.
- When not to inject: absolute contraindications are infection at the needle site, septic arthritis or osteomyelitis, fracture and a prosthetic joint. Relative ones include the HIV drug ritonavir, surgery planned within 4 weeks, previous blurred vision with steroids, very high blood glucose and a previous allergic reaction. There are still no evidence-based limits on how often or how many times these injections can be given; specialty societies suggest at least 3 months between injections, and some authors suggest no more than 3–5 at a single site.
- Athletes: an International Olympic Committee consensus statement says corticosteroid injections are not indicated for same-day return to play or within 72 hours of competition, because of the risk of tendon weakening, and the review advises avoiding vigorous activity for at least 48 hours after an injection, partly because of the temporary adrenal suppression. Under the WADA rules, glucocorticoids given by any injectable route are prohibited in competition and washout periods apply, so athletes need to check timing with their anti-doping organisation and, where needed, apply for a Therapeutic Use Exemption.
The local anaesthetic is not entirely innocent either. Its toxicity to cartilage depends on dose and exposure time, it appears to add to the toxicity of the steroid when the two are combined, and animal studies suggest a similar additive effect on tendon cells. A systematic review cited by the AJR authors found bupivacaine at 0.5% or higher, the concentration used in the Inject trial, to be the most toxic to human cartilage in the lab, although what this means at the doses used in a single injection is still poorly understood. Accidental injection into a blood vessel can also cause systemic toxicity, one more reason these procedures are done under image guidance.
The cost paradox
The health economic analysis adds a twist. Over a year, the steroid injection was less costly than sham from a societal perspective, with similar quality-adjusted life years, and had a more than 90% probability of being cost-effective at willingness-to-pay thresholds of AUD 50,000 and 100,000. The saving came from less time off work in the first 12 weeks and lower healthcare costs in the last six months. The injection without steroid had a low probability of being cost-effective (under 60%). The authors are cautious (and rightly so!), though: the QALY differences were very small and the health benefit negligible, so this is a modest economic signal rather than a clinical argument for the injection.
How I read it
For me, this is a very well-designed trial and an important one. A few things stand out.
The primary answer is no difference. Adding a high-volume injection, with or without steroid, to a good rehabilitation programme did not change pain and function at one year. That is the result that should guide practice, and the secondary findings do not change it.
The volume is not the active ingredient. The steroid-free injection tests the mechanical “break the neovessels” idea on its own, and it did nothing measurable to symptoms or to the tendon on ultrasound. This agrees with the 2020 BMJ trial by van der Vlist and colleagues, which also found no benefit of the steroid-free injection over sham up to 26 weeks; Inject extends that to 12 months. Earlier positive results came from much smaller trials by Boesen and colleagues (2017 and 2019); for the 2019 trial of 28 people, the Inject authors point out that the small sample raises concerns about overestimated effects and that using saline as the sham may have compromised masking.
Any steroid effect follows a familiar pattern. A possible small, short-lived benefit followed by worse outcomes later is what we have seen with corticosteroid injections in other tendinopathies, particularly lateral elbow. Here it was seen with a low dose (25 mg hydrocortisone) delivered around, not into, the tendon. In his accompanying editorial, John Orchard (University of Sydney) makes the practical point that corticosteroids are neither uniformly good nor uniformly bad: their use depends on whether short-term needs outweigh longer-term ones, patients should never be told an injection will “fix” tendinopathy, and clinicians need to explain that trade-off. The authors give a similar example: a self-employed person under financial pressure may reasonably value a few pain-free weeks.
The authors’ own prior beliefs make the result more convincing. One author is a radiologist working in a clinic that offers high-volume injections, and two physiotherapist authors, including the lead author, declare that they have recommended the injection in the past. Running a trial with a well-designed sham, publishing the analysis plan first, sharing the data and code openly, and then reporting a null result is exactly how it should be done, so kudos to the authors.
Rehabilitation that includes resistance exercise remains the backbone. Every participant received the same structured loading programme and education. The time and effort should go into well-dosed, progressive tendon loading, load management and patient education rather than into injections.
Limitations worth keeping in mind
- It is a single-centre trial and participants were recruited mainly through social media, so they may not represent people seeking care in hospital or clinic settings.
- The nurse and radiologists delivering the injections could not be masked, although they followed a scripted protocol to limit any influence.
- With many outcomes and time points, some of the secondary findings could reflect chance rather than true effects.
- Only the VISA-A was used from the four instruments in the newer core outcome set for Achilles tendinopathy, COVID-19 restrictions increased missing imaging and strength data, and adverse events and costs were self-reported every six weeks, which may be subject to recall bias.
- Half the participants had symptoms on both sides but only the worse side was injected.
- The population was middle-aged with long-standing symptoms. Whether the results apply equally to younger, high-level athletes with a shorter history is not known.
Bottom line
There was no difference between treatments at 12 months: high-volume injections, with or without corticosteroid, are no better than a sham injection when added to good rehabilitation for midportion Achilles tendinopathy. The steroid version may give a small, short-lived benefit at six weeks but is followed by worse outcomes than the steroid-free injection at six months. In the authors’ words, the evidence “should prompt clinicians to reconsider the rationale for using these injections in people with Achilles tendinopathy”, and the clinical data do not support routine use.

Reference: Malliaras P, Connell D, Boesen AP, Kearney RS, Menz HB, Morrissey D, Munteanu SE, Silbernagel KG, Underwood M, Forbes A, Haines TP. Efficacy and cost effectiveness of high volume injections with and without corticosteroid compared with sham for midportion Achilles tendinopathy (Inject trial): randomised controlled trial. BMJ 2026;395:e100807. https://doi.org/10.1136/bmj-2026-100807 (open access). Data and code: https://doi.org/10.26180/c.8671176.
Side effects review: Kamel SI, Rosas HG, Gorbachova T. Local and systemic side effects of corticosteroid injections for musculoskeletal indications. AJR 2024;222:e2330458. https://doi.org/10.2214/AJR.23.30458
Trial protocol: Malliaras P, et al. BMJ Open Sport & Exercise Medicine 2021;7:e001136. https://doi.org/10.1136/bmjsem-2021-001136. Trial registration: ACTRN12619001455156.


You must be logged in to post a comment.