Over the summer I wrote about the Lactate Threshold Analyzer and then about the anaerobic speed reserve, maximum speed and 3- and 5-zone models. Since then I have kept working on the second half of the tool, the Interval Session Designer, because turning a threshold into a good session is where most coaches actually need help. This post is a quick tour of what has changed.
The app as it looks today, with the sample runner’s step test loaded.
Session formats from a network meta-analysis
The headline change is that the designer now offers eight session formats, taken from the network meta-analysis by Held and colleagues (2026) comparing HIIT protocol designs on accumulated time at or above 90% of V̇O2max. Alongside the classic custom designer you can now pick even long intervals (the reference format in the review), even short intervals, short-interval blocks, 1:1 blocks, decreasing intensity, varied intensity and decreasing duration.
Choosing a format loads the protocol structure used in the studies behind it, and then translates it into speeds, paces and heart rates for your athlete. You can anchor the work on maximal aerobic speed, on the threshold you selected from the test, or on critical velocity if you have it from a separate test. If you choose critical velocity and do not enter one, the app tells you it is falling back on the 4 mmol·L−1 velocity and that the targets may be a little conservative. Every value is editable, and there is a button to reset back to the protocol used in the review.
The eight session formats, here with decreasing-duration intervals selected: 3, 2, 1 min, 45 s and 30 s of work with shrinking recoveries.
Below the inputs, the designer builds a step-by-step prescription table (time, target speed, pace and heart rate for every work and recovery bout) and a plot of the intensity profile of the whole session. The heart rate targets come from the athlete’s own heart rate–speed relationship in the test, capped at HRmax, with a reminder that during short supramaximal bouts heart rate lags and will not reach those values.
The evidence, shown honestly
This is the part I care about most. Each format comes with its own evidence panel: the effect size against even long intervals with its confidence interval, the P-score ranking, how many protocol arms it rests on, the certainty of the evidence, and the actual protocols used in the studies. A small forest plot shows where every format sits.
The intensity profile of the session and the evidence panel underneath it.
The P-scores look tempting. Decreasing duration ranks top at 89.6%, varied intensity at 76.7%, decreasing intensity at 68.4%. But I did not want the app to turn a ranking into a recommendation. In the review, no format was significantly better than even long intervals, the certainty of evidence is very low, and the top-ranked format rests on just two protocol arms from the same research group, with sessions that were not time-matched to the comparison. The app says all of this next to the numbers, not in a footnote. My advice is the same as the review’s: pick the format on feasibility, the athlete’s profile and matching the workload, and treat the ranking as exploratory.
A ranking is not a recommendation. The evidence panel is there so coaches can see how much, or how little, sits behind each choice.
Choosing the anchor that drives everything
The threshold comparison table now lets you tap any of the six detection methods (V4/OBLA from the curve or by linear interpolation, LT at baseline +0.4 mmol·L−1, Dmax, modified Dmax and the log-log turnpoint) to make it the anchor. Training zones and interval targets update straight away, so you can see how much a choice of method changes the prescription before you commit to one.
Six threshold methods side by side, with the selected one driving the 3- or 5-zone model.
What’s next
I am now working on turning the tool into an iOS and Android app, with athlete and test history, pitch-side data entry, PDF and CSV export, and club or clinic branding. I will post here when it is ready. In the meantime the web version is free to use and nothing needs installing. As always, if you use it and something looks wrong or you would like a feature, let me know.
Held, S., Rappelt, L., Micke, F., Wiedenmann, T., & Donath, L. (2026). Comparison of high-intensity interval training protocol designs on accumulated time ≥ 90% V̇O2max: a network meta-analysis. BMC Sports Science, Medicine and Rehabilitation, 18, 336. https://doi.org/10.1186/s13102-026-01891-7
The tool is intended for education and performance monitoring. Thresholds, zones and session targets should be interpreted alongside the athlete’s full physiological and training profile.
Achilles tendinopathy is one of those conditions every sports medicine team knows too well. Around 6% of people will have it at some point in their lives, 38% of workers affected report reduced work capacity, and exercise-based rehabilitation, the recommended first-line treatment, does not resolve the problem in up to 44% of cases. While I personally solved such issues always with resistance exercise, almost half of those with persistent symptoms go on to seek other treatments, and injections are a common next step. One of the most popular over the last 15 years has been the high-volume injection: 50 mL of fluid pushed in between the tendon and the fat pad that sits in front of it, often with a corticosteroid added.
A randomised controlled trial just published in The BMJ by Peter Malliaras and colleagues, the Inject trial (28 October 2026), gives us the best data so far on whether these injections work. The headline is clear: at 12 months there was no difference between treatments. Neither the high-volume injection with corticosteroid nor the one without it improved pain and disability compared with a sham injection, and the two injections did not differ from each other.
What the trial did
The team randomised 192 adults with midportion Achilles tendinopathy at a radiology clinic in Melbourne between December 2019 and July 2022, recruited mainly through paid social media advertising and referrals from local doctors and physiotherapists. These were not mild cases: mean age 49, 55% men, a median symptom duration of two years, a baseline VISA-A score of 48.7 out of 100, about half with symptoms in both legs and a third with obesity. Everyone had pain for at least three months, ultrasound evidence of tendon pathology (hypoechoic areas and/or Doppler signal), and had not responded to previous treatment; almost 80% had already tried exercise.
Participants were randomised 1:1:1 to one of three arms:
Sham injection (n = 64)
High-volume injection without corticosteroid (n = 63)
High-volume injection with corticosteroid (n = 65)
Crucially, everyone then received the same care from a physiotherapist: a progressive 12-week calf and Achilles loading programme, education on activity modification using a pain-monitoring model, and information about the condition and its prognosis. So the question the trial answers is not “injection versus nothing” but “does adding an injection to good rehabilitation make a difference?”. Adherence was high, with 91–95% of participants averaging at least two exercise sessions a week across groups.
The primary outcome was the VISA-A (Victorian Institute of Sport Assessment – Achilles, 0–100, higher is better) at 52 weeks, and the trial was powered to detect a 10-point difference between any two groups. Because there were three pairwise comparisons, the authors used 98.33% confidence intervals and a significance threshold of 0.0167. A full cost-utility analysis from a societal perspective ran alongside, and the statistical analysis plan was published before any analysis started.
The injections, explained
The high-volume injection was introduced by Otto Chan and colleagues in 2008. Its rationale is that part of the pain in Achilles tendinopathy comes from new blood vessels and nerves growing into the front of the tendon from Kager’s fat pad, the triangle of fat between the Achilles, the deep flexor tendons and the heel bone. Injecting a large volume of fluid exactly at that interface is thought to disrupt this neurovascular ingrowth mechanically or by temporarily reducing blood supply, while a corticosteroid, when added, provides an anti-inflammatory effect.
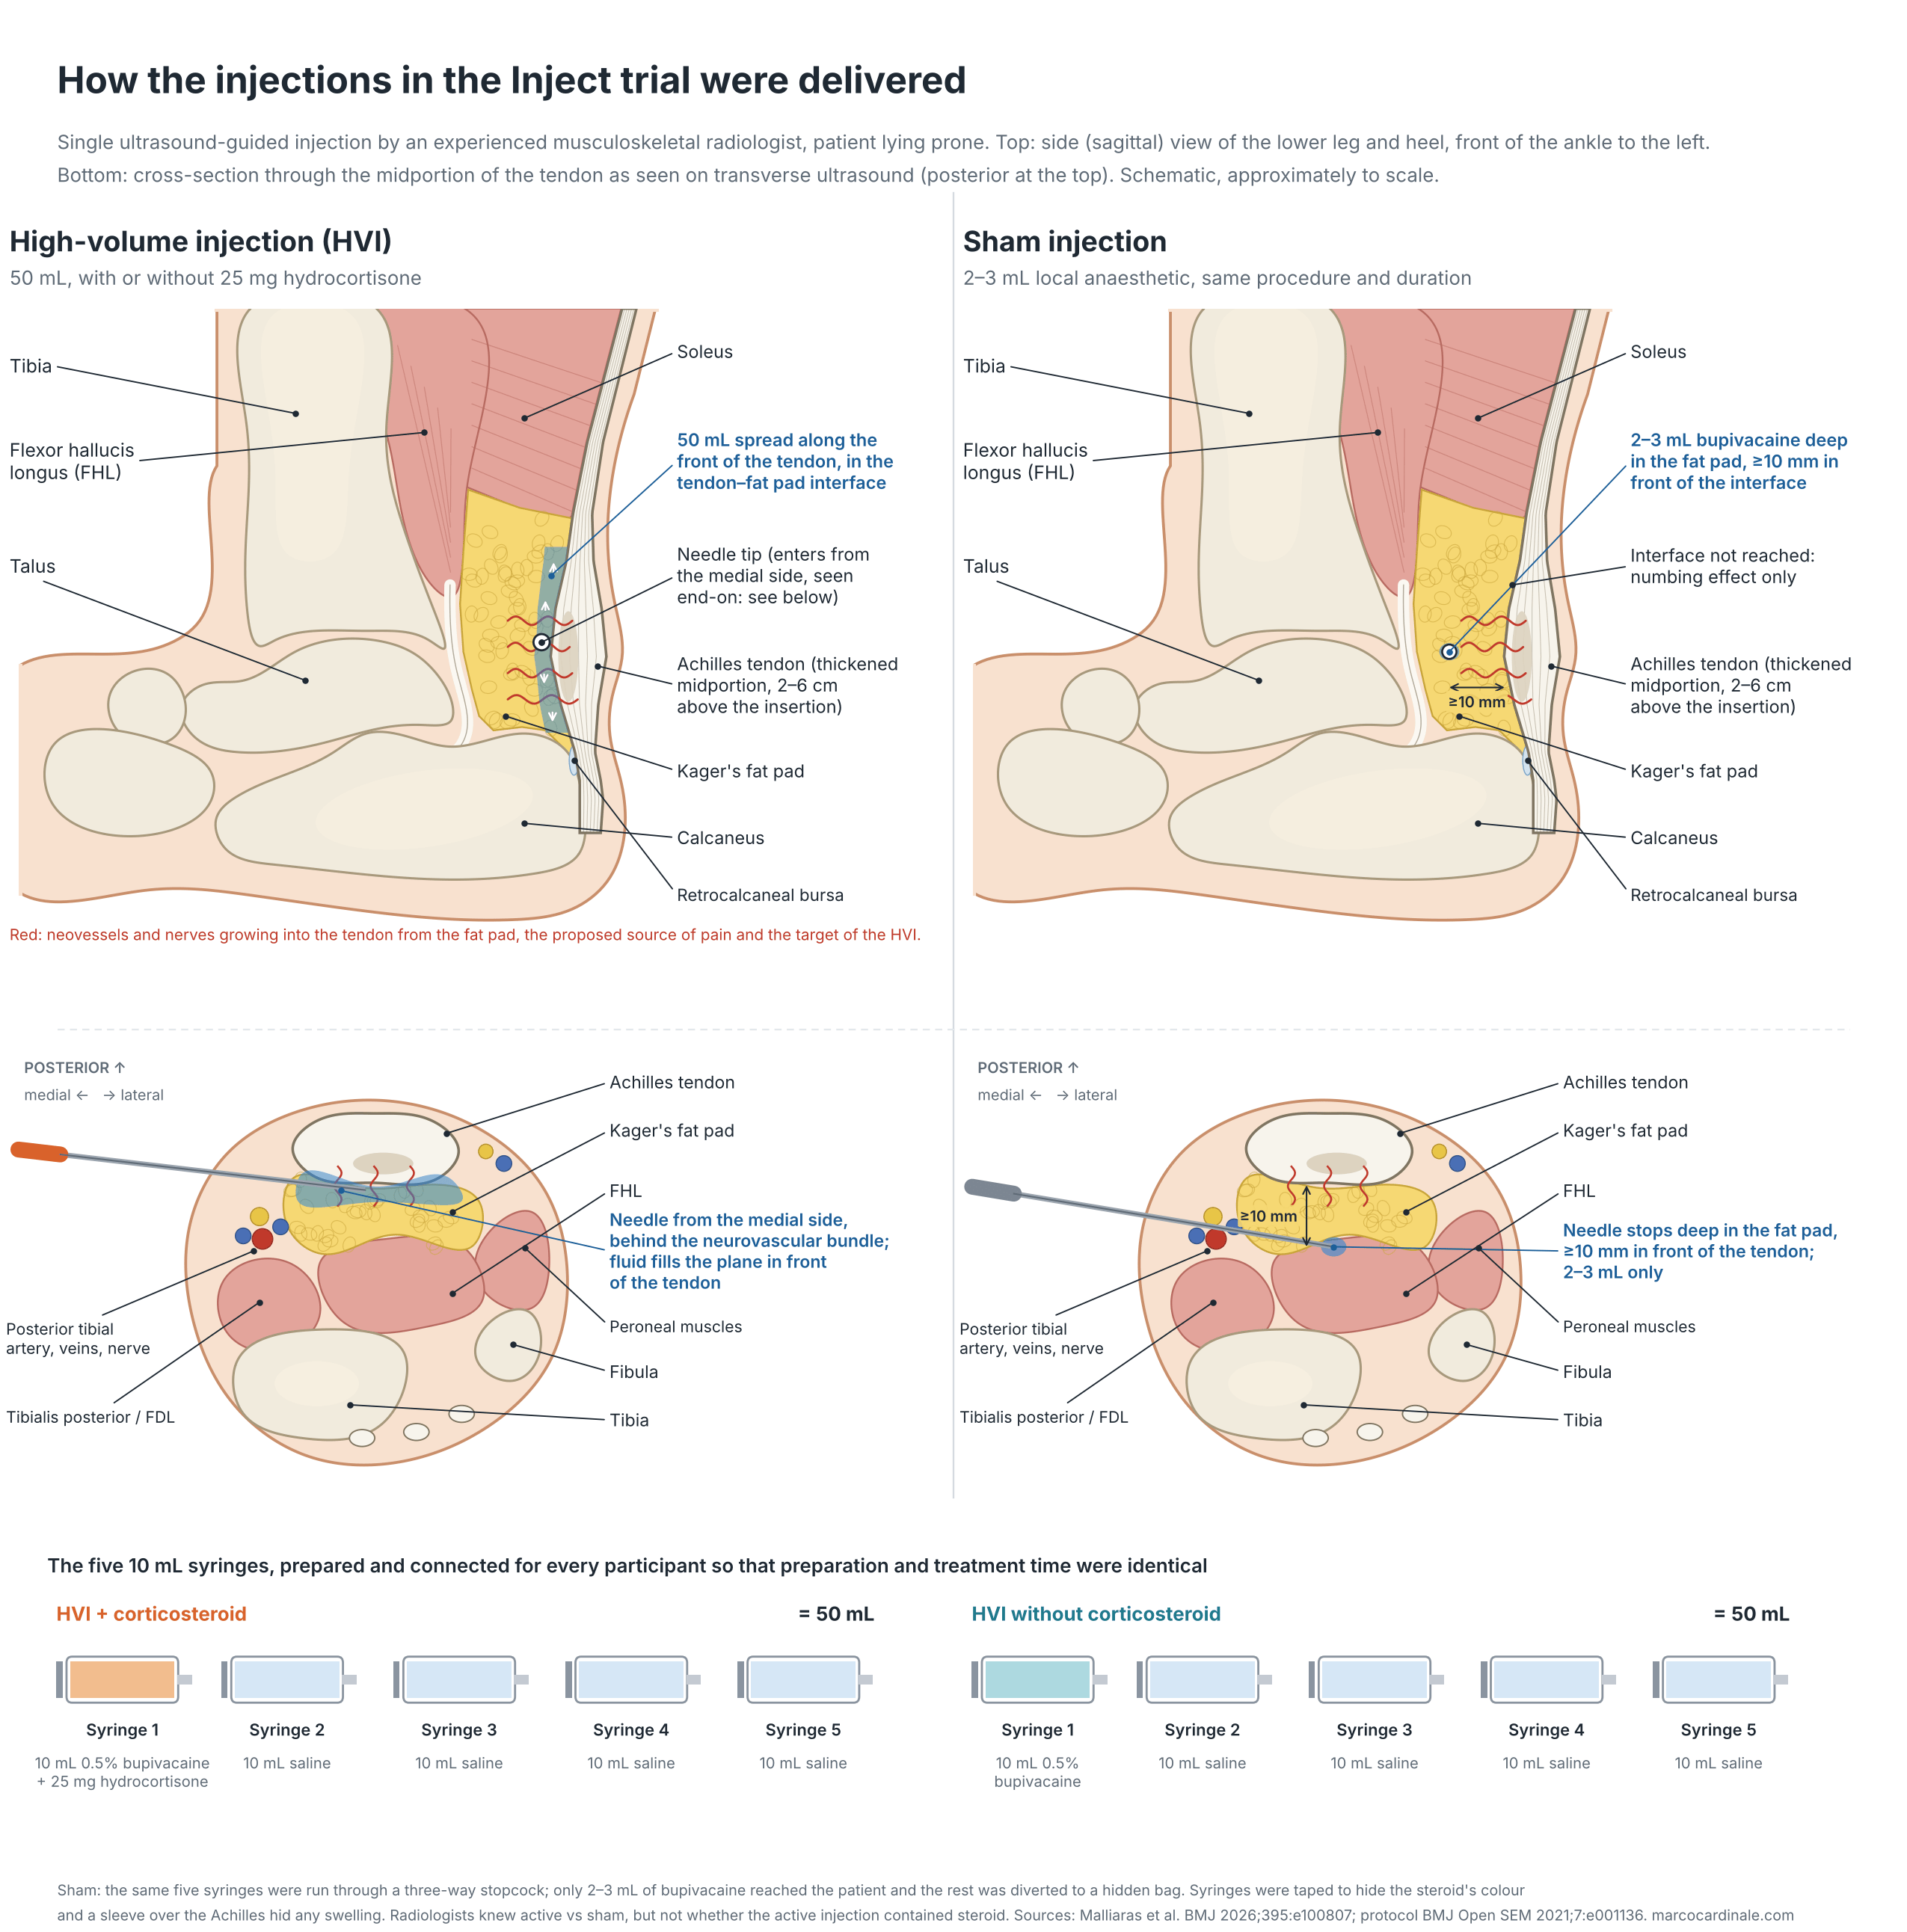
Each participant received a single injection, under ultrasound guidance, from one of three experienced musculoskeletal radiologists, with the patient lying face down. Dr Chan himself travelled to Melbourne to train the radiologists, and 11% of injections were randomly observed to check fidelity. In practice:
High-volume injection with corticosteroid: five 10 mL syringes connected in sequence through a tube. The first contained 10 mL of 0.5% bupivacaine (a local anaesthetic) with 25 mg of hydrocortisone, followed by four syringes of 10 mL normal saline, for a total of 50 mL. The needle was placed at the interface between Kager’s fat pad and the tendon and moved gently along it, under continuous ultrasound monitoring, to spread the fluid evenly over the pathological area.
High-volume injection without corticosteroid: identical, except the first syringe contained only the 10 mL of bupivacaine.
Sham injection: 2–3 mL of 0.5% bupivacaine, injected at least 10 mm anterior to (deeper than) the fat pad–tendon interface, a placement unlikely to be therapeutic. It produces a numbing effect similar to the high-volume injections.
The masking procedures are worth noting. Every participant went through an identical procedure with five 10 mL syringes. In the sham group, a three-way stopcock diverted the fluid to a hidden bag. The syringes were taped so the colour of the steroid could not be seen, and afterwards participants wore a sleeve over the Achilles to hide any swelling from the large volume. The radiologists knew whether they were giving an active or a sham injection, but not whether the active one contained steroid. The check worked: immediately after the injection, 67–73% of participants in each group were unsure what they had received, and only 22–24% in each group believed they had received an active injection.
How the injections were delivered: side view, ultrasound cross-section and syringe contents (schematic; click to enlarge).
What each ingredient does
Bupivacaine is a long-acting local anaesthetic. It blocks voltage-gated sodium channels in nerve fibres, so pain signals cannot be transmitted. Its peak effect comes after about 30–45 minutes and the numbness lasts hours, not weeks. In the trial it gave the same numbing sensation in all three arms, which is part of what kept participants unaware of their group. The 50 mg used in the high-volume injections is well below the usual maximum dose of about 2 mg/kg (up to 175 mg), and the sham delivered 10–15 mg.
Hydrocortisone is a corticosteroid. It diffuses into cells, binds the glucocorticoid receptor and switches genes off and on in the nucleus: it dampens the NF-κB-driven production of inflammatory cytokines and COX-2, and increases annexin A1, which blocks phospholipase A2 and therefore the production of prostaglandins and leukotrienes. The net result is less inflammation, less vascular leakage and less pain sensitisation. The same actions have a cost in tendon tissue: injected corticosteroids reduce local collagen production, which can limit healing and leave the tendon more prone to failure. Hydrocortisone is short-acting and the least potent of the injectable steroids: 25 mg is equivalent to about 5 mg of triamcinolone, compared with the 40 mg typically injected into a large joint. Because tendinopathy is thought to be more a failed healing response than classic inflammation, damping that response can ease pain early without rebuilding the tendon.
Saline provides the volume: 40 mL meant to separate the tendon from the fat pad and disrupt the neovessels and nerves, mechanically or by cutting their blood supply. In Inject, the steroid-free injection made no difference to symptoms, Doppler signal or tendon thickness, so the volume on its own seems to be inactive.
How the drugs in a high-volume injection work, and the benefits and risks of corticosteroid injections (click to enlarge).
What they found: no difference between treatments
Follow-up was excellent, with VISA-A data from 181 of 192 participants (94%) at 12 months. At the primary endpoint there was no difference between any of the groups:
High-volume injection with corticosteroid vs sham: −3.5 points (98.33% CI −12.0 to 5.0)
High-volume injection without corticosteroid vs sham: +4.0 points (−4.2 to 12.3)
With vs without corticosteroid: −7.5 points (−15.3 to 0.3)
The high-volume injection without steroid showed no benefit over sham at any time point, on VISA-A or on any secondary outcome. Ultrasound told the same story: there were no differences in Doppler signal or tendon thickness between this injection and sham. As the authors put it, simply injecting a volume of fluid does not seem to affect tendon pathology or improve clinical outcomes.
The secondary time points showed a pattern worth knowing about, but it needs to be read with caution. With the steroid injection there was a small benefit over sham at six weeks (+9.2 points, 1.5 to 16.9), together with a better global rating of change. By 26 weeks the steroid group was doing worse than the group that had received the same injection without steroid (−8.6 points, −16.4 to −0.7), with higher worst pain over the previous week (11.3 points on a 0–100 scale). All of these differences were smaller than the 10-point target, and the authors note that the early benefit is unlikely to be clinically meaningful and might be no more than chance, given the number of outcomes and time points tested.
Between-group differences in VISA-A with 98.33% confidence intervals.
Benefits and risks of these injections
Benefits. The case for a corticosteroid-containing injection rests on short-term relief. In the Inject trial this was a 9.2-point VISA-A advantage over sham at six weeks, smaller than the 10-point target and gone by 12 months, along with less time off work early on and lower costs over the year. The procedure is quick, done in one visit and image-guided. The steroid-free injection showed no benefit at any point.
Risks in the trial. There were no Achilles tendon ruptures. Six participants had serious adverse events (two in each group), none related to the trial. Non-serious adverse events were common in all groups (53% sham, 38% without steroid, 49% with steroid), mostly aggravated Achilles pain (28%, 16% and 25%) or other musculoskeletal pain. Only one, injection-site pain after the steroid injection, was judged to be related to the injection itself. The main harm signal was clinical rather than a complication: worse VISA-A and worse pain at 26 weeks with the steroid than without it.
Risks of corticosteroid injections in general. A 2024 review in the American Journal of Roentgenology by Kamel, Rosas and Gorbachova sets out the side effects patients should be told about before a musculoskeletal steroid injection. It also notes that systematic reviews are inconclusive on long-term benefit for joints and tendinopathy, which fits the Inject results. Most of the frequencies below come from mixed injection sites, often joints, rather than from Achilles injections specifically:
Local: a post-injection flare of pain is common, reported in 33–35% of hand, wrist and shoulder injections, usually starting 1–2 days later and lasting about 2 days. Skin thinning or loss of colour occurs in up to 10% after superficial injections (for example of the plantar fascia), appears within months and usually resolves within a year. Tendon rupture is rare, about 0.1%, typically between 2 days and 6 weeks after the injection, and the Achilles is one of the tendons involved in case reports. Being next to the tendon rather than in it is not a guarantee of safety: in a rabbit study, injection into the retrocalcaneal bursa weakened the Achilles as much as injection into the tendon. Infection after a joint injection is very rare (under 0.001%), and soft-tissue calcification, faster progression of osteoarthritis and bone injury have also been reported, mainly after joint injections.
Systemic: part of the injected steroid reaches the bloodstream. Cortisol production is suppressed for at least a week after a single injection, and for up to 2 weeks in a study of young athletes. Facial flushing affects about 40% and settles within 3 days. Blood pressure and blood glucose can rise for more than a week. About half of premenopausal women have early or delayed periods afterwards. Allergic reactions (0.3–0.5%), raised eye pressure, insomnia, headache and, with repeated use, bone loss are also described.
People with diabetes: glucose typically peaks 1–3 days after the injection, and levels up to 500 mg/dL have been reported. The review cites a recommendation to check glucose twice a day for a week, seek help above 360 mg/dL, and avoid injecting if fasting glucose is above 200–250 mg/dL.
Surgery: injections are linked to more post-operative infections and to more revision surgery after tendon repair. The review suggests delaying surgery for 1–3 months after an injection and withholding steroid for 3–6 months before a tendon repair or joint replacement.
When not to inject: absolute contraindications are infection at the needle site, septic arthritis or osteomyelitis, fracture and a prosthetic joint. Relative ones include the HIV drug ritonavir, surgery planned within 4 weeks, previous blurred vision with steroids, very high blood glucose and a previous allergic reaction. There are still no evidence-based limits on how often or how many times these injections can be given; specialty societies suggest at least 3 months between injections, and some authors suggest no more than 3–5 at a single site.
Athletes: an International Olympic Committee consensus statement says corticosteroid injections are not indicated for same-day return to play or within 72 hours of competition, because of the risk of tendon weakening, and the review advises avoiding vigorous activity for at least 48 hours after an injection, partly because of the temporary adrenal suppression. Under the WADA rules, glucocorticoids given by any injectable route are prohibited in competition and washout periods apply, so athletes need to check timing with their anti-doping organisation and, where needed, apply for a Therapeutic Use Exemption.
The local anaesthetic is not entirely innocent either. Its toxicity to cartilage depends on dose and exposure time, it appears to add to the toxicity of the steroid when the two are combined, and animal studies suggest a similar additive effect on tendon cells. A systematic review cited by the AJR authors found bupivacaine at 0.5% or higher, the concentration used in the Inject trial, to be the most toxic to human cartilage in the lab, although what this means at the doses used in a single injection is still poorly understood. Accidental injection into a blood vessel can also cause systemic toxicity, one more reason these procedures are done under image guidance.
The cost paradox
The health economic analysis adds a twist. Over a year, the steroid injection was less costly than sham from a societal perspective, with similar quality-adjusted life years, and had a more than 90% probability of being cost-effective at willingness-to-pay thresholds of AUD 50,000 and 100,000. The saving came from less time off work in the first 12 weeks and lower healthcare costs in the last six months. The injection without steroid had a low probability of being cost-effective (under 60%). The authors are cautious (and rightly so!), though: the QALY differences were very small and the health benefit negligible, so this is a modest economic signal rather than a clinical argument for the injection.
How I read it
For me, this is a very well-designed trial and an important one. A few things stand out.
The primary answer is no difference. Adding a high-volume injection, with or without steroid, to a good rehabilitation programme did not change pain and function at one year. That is the result that should guide practice, and the secondary findings do not change it.
The volume is not the active ingredient. The steroid-free injection tests the mechanical “break the neovessels” idea on its own, and it did nothing measurable to symptoms or to the tendon on ultrasound. This agrees with the 2020 BMJ trial by van der Vlist and colleagues, which also found no benefit of the steroid-free injection over sham up to 26 weeks; Inject extends that to 12 months. Earlier positive results came from much smaller trials by Boesen and colleagues (2017 and 2019); for the 2019 trial of 28 people, the Inject authors point out that the small sample raises concerns about overestimated effects and that using saline as the sham may have compromised masking.
Any steroid effect follows a familiar pattern. A possible small, short-lived benefit followed by worse outcomes later is what we have seen with corticosteroid injections in other tendinopathies, particularly lateral elbow. Here it was seen with a low dose (25 mg hydrocortisone) delivered around, not into, the tendon. In his accompanying editorial, John Orchard (University of Sydney) makes the practical point that corticosteroids are neither uniformly good nor uniformly bad: their use depends on whether short-term needs outweigh longer-term ones, patients should never be told an injection will “fix” tendinopathy, and clinicians need to explain that trade-off. The authors give a similar example: a self-employed person under financial pressure may reasonably value a few pain-free weeks.
The authors’ own prior beliefs make the result more convincing. One author is a radiologist working in a clinic that offers high-volume injections, and two physiotherapist authors, including the lead author, declare that they have recommended the injection in the past. Running a trial with a well-designed sham, publishing the analysis plan first, sharing the data and code openly, and then reporting a null result is exactly how it should be done, so kudos to the authors.
Rehabilitation that includes resistance exercise remains the backbone. Every participant received the same structured loading programme and education. The time and effort should go into well-dosed, progressive tendon loading, load management and patient education rather than into injections.
Limitations worth keeping in mind
It is a single-centre trial and participants were recruited mainly through social media, so they may not represent people seeking care in hospital or clinic settings.
The nurse and radiologists delivering the injections could not be masked, although they followed a scripted protocol to limit any influence.
With many outcomes and time points, some of the secondary findings could reflect chance rather than true effects.
Only the VISA-A was used from the four instruments in the newer core outcome set for Achilles tendinopathy, COVID-19 restrictions increased missing imaging and strength data, and adverse events and costs were self-reported every six weeks, which may be subject to recall bias.
Half the participants had symptoms on both sides but only the worse side was injected.
The population was middle-aged with long-standing symptoms. Whether the results apply equally to younger, high-level athletes with a shorter history is not known.
Bottom line
There was no difference between treatments at 12 months: high-volume injections, with or without corticosteroid, are no better than a sham injection when added to good rehabilitation for midportion Achilles tendinopathy. The steroid version may give a small, short-lived benefit at six weeks but is followed by worse outcomes than the steroid-free injection at six months. In the authors’ words, the evidence “should prompt clinicians to reconsider the rationale for using these injections in people with Achilles tendinopathy”, and the clinical data do not support routine use.
The Inject trial at a glance (click to enlarge).
Reference: Malliaras P, Connell D, Boesen AP, Kearney RS, Menz HB, Morrissey D, Munteanu SE, Silbernagel KG, Underwood M, Forbes A, Haines TP. Efficacy and cost effectiveness of high volume injections with and without corticosteroid compared with sham for midportion Achilles tendinopathy (Inject trial): randomised controlled trial. BMJ 2026;395:e100807. https://doi.org/10.1136/bmj-2026-100807 (open access). Data and code: https://doi.org/10.26180/c.8671176.
Side effects review: Kamel SI, Rosas HG, Gorbachova T. Local and systemic side effects of corticosteroid injections for musculoskeletal indications. AJR 2024;222:e2330458. https://doi.org/10.2214/AJR.23.30458
Trial protocol: Malliaras P, et al. BMJ Open Sport & Exercise Medicine 2021;7:e001136. https://doi.org/10.1136/bmjsem-2021-001136. Trial registration: ACTRN12619001455156.
For more than a decade we have been collecting data from wearables at an incredible rate: steps, heart rate, heart rate variability, sleep, GPS traces, training sessions. Yet the step that matters most has always been the hardest one: going from numbers to a decision. What should this person do next week, given their data, their health history and their life? In high-performance sport we solve that problem with teams of people. For the general population, that team simply does not exist.
A paper just published in Nature by Heydari and colleagues at Google Research, “The anatomy of a personal health agent” (21 October 2026), is the most serious attempt I have seen so far to build that team in software. It is worth reading carefully, both for what it shows and for what it does not show, because it gives us a realistic preview of AI-generated, personalised activity prescriptions based on our own data.
What they built
The authors started from users rather than from technology. They analysed 1,370 real consumer health queries from search, Gemini and the Fitbit forum, surveyed 555 people using an experimental Fitbit Labs chatbot and ran a workshop with 14 experts. Four types of need emerged: general health knowledge, interpretation of personal data, wellness advice, and symptom assessment. These needs require very different skills — numerical precision and code for data questions, factual grounding for knowledge and symptoms, empathetic open-ended dialogue for coaching — and the team found that a single large language model struggled to balance them.
Their solution is a modular, multi-agent system — the Personal Health Agent (PHA) — built on Gemini 2.0, made of three specialists coordinated by an orchestrator:
A data science agent that turns a vague question (“am I getting fitter?”) into an explicit analysis plan, then writes and runs Python code on the user’s wearable time series, including comparisons with population percentiles by age and sex.
A domain expert agent that reasons over wearable data, blood tests and health history, using tools such as NCBI literature search, web search and population statistics to ground its answers.
A health coach agent built around motivational interviewing: it identifies goals first, explores constraints, asks for feedback and only then offers a SMART recommendation.
The orchestrator decides which agent leads and which ones support, rewrites a targeted sub-question for each, checks the combined answer for coherence (and to avoid asking the user for data it already has), and keeps a memory of goals, barriers and preferences across turns.
What the evaluation shows
The evaluation is large: 11 benchmark tasks, more than 7,000 annotations and about 1,350 hours of work from end users and experts, grounded in the WEAR-ME study (1,165 Fitbit users with blood tests and questionnaires). A few results stood out for me.
Data analysis. The data science agent’s analysis plans scored 75.6% against 53.7% for the base model. The most striking gain was in checking whether there was enough data to answer the question in the first place: 66.5% of plans did so, against just 5.3% for the base model. Anyone who has worked with wearable data knows that missing days, non-wear periods and artefacts are where most bad conclusions come from. Its code passed 75.5% of expert-written unit tests at the first attempt (58.4% for the base model), rising to 79% with self-correction.
Health knowledge and context. On more than 2,000 board-style questions in endocrinology, cardiology, sleep medicine and strength and conditioning, the gain over the base model was small (83.6% vs 81.8%). Much bigger differences appeared when personal context mattered: end users rated 96.9% of the domain expert’s personalised answers as trustworthy against 38.7% for the base model, and five clinicians judged 65% of its multimodal health summaries useful against 30%.
Coaching. Users preferred the coach agent on five of six coaching themes, and expert coaches preferred it on all six. Interestingly, both groups gave the plain baseline a slight edge on progress measurement — a weakness the authors then addressed in the integrated system.
The integrated agent. In live multi-turn conversations, 45 users role-playing real WEAR-ME profiles ranked the orchestrated PHA first 46.7% of the time, against 28.9% for a parallel multi-agent design and 24.4% for a single agent. The experts were far more decisive: the PHA was ranked best in 66.7% of conversations, roughly five times as often as the single agent, with an overall quality score of 72.8% against 64.3% and 54.4%.
Why this matters for activity prescription
What struck me most is that the architecture mirrors how a good performance support team works. Someone looks at the data properly, someone interprets it in the context of the person’s health and history, and someone turns it into a plan the person will actually follow. Exercise prescription needs all three. Frequency, intensity, time and type are not chosen from a guideline table alone; they depend on where the person is starting from, what they can safely tolerate, and what they are willing and able to do.
Seen through that lens, the near-future pipeline is easy to imagine:
Baseline from your own data: real habitual steps, active minutes, resting heart rate, HRV and sleep — computed, not guessed, and checked for missing data.
Comparison and context: where you sit relative to people of your age and sex, and what your blood markers and conditions mean for what is safe.
A negotiated dose: a first step that fits your constraints and motivation rather than a generic “150 minutes a week”.
Progression: memory of what was agreed and what actually happened, so the next prescription builds on the last one.
The example conversation in the paper’s extended data shows this already. A user with type 2 diabetes, a BMI of about 36, around 5,500 steps per day and a recent hospital admission asks how to get back to 10,000 steps. Instead of prescribing the target, the agent explores why it matters to her, picks up symptoms that suggest possible sleep apnoea, recommends speaking to her doctor, and agrees on several short 10-minute walks per day as a starting point. That is, in essence, a graded prescription with a red-flag screen built in. Another example I liked: asked whether more activity leads to more deep sleep, the data science agent reported a correlation of about 0.14 and said plainly that the relationship was weak — exactly the kind of honest answer a good analyst gives and a lot of consumer apps do not.
The real opportunity is scale. One practitioner cannot review thousands of people’s data every day and adjust their plan. A system like this could make the first layer of individualised prescription and follow-up available to anyone wearing a device, and free human experts to focus on the people and decisions that need them.
The risks we should not gloss over
The authors are refreshingly upfront about limitations, and they describe the PHA as a research prototype rather than a clinical tool. Still, for anyone tempted to treat this as a ready-made prescription engine, these are the issues I would keep in mind.
Safety at scale. In the expert safety review of the clinical summaries, 83% carried no or minimal potential for harm, but 15% were judged mildly harmful and 2% moderately to severely harmful. Two per cent sounds small until it is multiplied by millions of users.
No outcome data. Everything measured is conversation quality and short-term task performance. There is no evidence yet that people change behaviour, get fitter or become healthier. For an activity prescription, the only test that ultimately matters is the dose–response over weeks and months.
Data quality and generalisability. The data come from one device ecosystem (Fitbit), and consumer estimates of sleep stages or HRV have their own validity limits. Even the improved agent checked data sufficiency in only two-thirds of its plans, so one-third did not.
Simulated users. In the live studies, participants role-played personas matched to their own profiles rather than seeking help for themselves, and parts of the evaluation relied on LLM-based autoraters. Both are reasonable research choices, but neither is the real world.
Training load is not in scope. The system was not evaluated on periodisation, load management, injury risk, environmental stress such as heat, or athletic populations. Extending it to performance settings needs its own validation.
Evidence quality. Open-web retrieval can surface weak or conflicting evidence. The authors themselves suggest restricting retrieval to curated sources and showing provenance next to every recommendation.
Privacy, equity and cost. Real deployment needs proper privacy and security controls, fairness checks across populations, languages and literacy levels, and a cheaper architecture: the PHA averaged 6.5 model calls and about 205 seconds per response, against 3 calls and 36 seconds for a single agent.
Who built and judged it. The work was funded by Alphabet, most authors are Google employees, and the system runs on Google models and Fitbit data. That does not invalidate the findings — and releasing the code and benchmark is a genuinely good step — but independent replication will matter.
Coaching versus prescribing. The coach agent sometimes declines to give a concrete number and steers the user to decide for themselves. Good motivational practice, but people asking for an exercise prescription often need a clear, specific dose — and someone accountable for it.
What I would want to see next
Before trusting an AI-generated activity prescription, I would want to know four things: whether it checked the quality of the data before drawing conclusions, whether its evidence comes from curated sources it shows me, whether it recognises red flags and hands off to a clinician rather than reassuring, and whether its prescriptions are reviewed against what actually changed over time. The next generation of studies should be prospective, longitudinal and outcome-based, with people using the system for themselves, across devices and populations, and with clinicians and coaches in the loop.
Bottom line
This paper does not show that AI can prescribe exercise better than a qualified professional. It shows something more modest and, I think, more important: that splitting the job into data analysis, domain expertise and coaching, and orchestrating them carefully, produces answers that experts judge to be substantially better than a single general model. Personalised activity prescriptions built from our own data are no longer a distant idea. The challenge now is to prove that they are safe and that they actually change behaviour and health — and to make sure the humans who are accountable for those decisions stay firmly in the loop.




You must be logged in to post a comment.